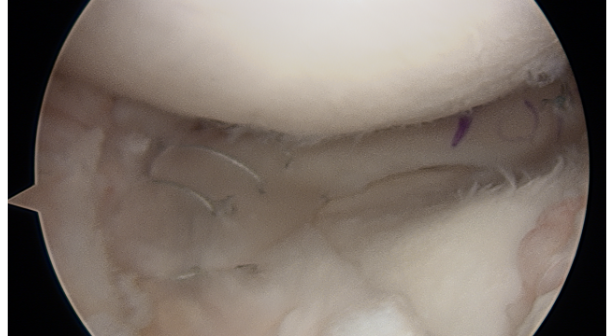
Meniscus Transplantation
Allograft meniscal transplantation for patients with irreparable meniscal loss to restore cushioning function and prevent osteoarthritis.
Overview
Meniscus transplantation uses donor tissue (allograft) to restore the cushioning function of the knee in patients with irreparable meniscal loss. This biological solution is particularly valuable in young, active patients to prevent premature joint degeneration. Successful transplantation requires careful patient selection, proper graft sizing, and secure fixation.
Indications
- Symptomatic meniscal deficiency following prior meniscectomy
- Failed meniscus repair
- Young patients with irreparable meniscal loss
- Prevention of postmeniscectomy osteoarthritis
Recovery
6-12 months for full recovery; return to sport 9-12 months
Success Rates
Meniscus transplantation demonstrates 80–90% graft survival at 10 years when appropriate patient selection and surgical technique are employed. Outcomes are best in younger patients with minimal degenerative changes and good compliance with rehabilitation.
Rehabilitation Programme
The goal of surgery is to relieve pain, increase joint stability and protect the joint surface. This is not a procedure that aims to return patients to high-intensity, pivoting or impact sport. It is common for other procedures to be performed simultaneously — such as ACL reconstruction or realignment osteotomy — and rehabilitation will be tailored accordingly.
Post-operative bracing is required and weight bearing is delayed for 6 weeks to allow meniscal healing to the tibial plateau. Range of motion and active extension are progressed more slowly to protect the healing meniscus and avoid undue strain at the root insertions.
| Phase / Time | Brace & Weight Bearing | ROM | Exercises & Modalities |
|---|---|---|---|
Phase I Weeks 0–6 Protection & ROM | Tracker brace 0–90°; worn 24 hours per day. Flat foot feather touch weight bearing with crutches. | 0–90°. |
Modalities: Ice compression therapy and IFC as needed to reduce pain and swelling. Compex/muscle stimulation to assist quadriceps activation. Blood flow restriction (BFR) therapy during strengthening exercises. |
Phase II Weeks 6–12 Weight Bearing & Strengthening | Advance to WBAT; wean off tracker brace and crutches, ensuring normal heel–toe gait. Transfer to Ossur Cartilage Rebound unloading brace. | Progress to full ROM as tolerated (flexion and extension). | If concomitant ACL, can transition to ACL rehabilitation protocol at this stage.
Modalities: Ice compression therapy as needed. Compex/muscle stimulation to assist muscle activation. Blood flow restriction (BFR) therapy during strengthening exercises. |
Phase III 3–6 Months Strength & Conditioning | Ossur Cartilage Rebound unloading brace until 6 months for activity. | Full and pain-free. |
Modalities: Blood flow restriction (BFR) therapy during strengthening exercises. |
Phase IV 6+ Months Return to Activity / Light Sport | As tolerated per surgeon guidance. | Full and pain-free. | Impact activities such as jogging/running may commence from 6 months onwards.
|
Phase I — Weeks 0–6
Protection & ROM
Brace & Weight Bearing
Tracker brace 0–90°; worn 24 hours per day. Flat foot feather touch weight bearing with crutches.
ROM
0–90°.
Exercises
- Weeks 0–2: Patellar mobilisations
- Heel slides (± slider board), calf & hamstring stretches
- Quad/ham co-contraction, gluteal activation (supine or standing), isometric hip adduction/abduction, ankle pumping
- Sitting passive leg extension with roll under heel if extension lag
- Weeks 2–6 add: Supine legs up wall — heel slides (knee flexion); supine legs on Swiss ball: knee flexion
- Bike pendulums: ½ circles forward/backward — lower seat as tolerated
- Quadriceps isometrics in long sitting and standing (± muscle stimulation)
- Non-weight bearing hip stability: abduction, extension, external rotation, clam shells, supine bridging on Swiss ball
- Ankle theraband plantar flexion, sitting calf raises
Modalities: Ice compression therapy and IFC as needed to reduce pain and swelling. Compex/muscle stimulation to assist quadriceps activation. Blood flow restriction (BFR) therapy during strengthening exercises.
Phase II — Weeks 6–12
Weight Bearing & Strengthening
Brace & Weight Bearing
Advance to WBAT; wean off tracker brace and crutches, ensuring normal heel–toe gait. Transfer to Ossur Cartilage Rebound unloading brace.
ROM
Progress to full ROM as tolerated (flexion and extension).
Exercises
If concomitant ACL, can transition to ACL rehabilitation protocol at this stage.
- Continue patellar mobilisations
- Low resistance stationary bike, progressing to full rotations
- Weight shifting: 2 scales 50–50 WB → progress to mini squats
- Leg extension (or quad over roll), active terminal knee extension with theraband
- Abdominal and core strengthening (curl-ups, transversus abdominis with SLR)
- Standing hip flexion/extension, abduction/adduction with weights/pulleys/bands
- Supine bridging: 2 → 1 leg Swiss ball bridge + knee flexion
- Shuttle/leg press: 2-leg squat/calf raises → progress 2 → 1 leg; increase ROM & resistance
- Mini wall squats (30–60°) → 60–90°; sit to stand
- Hamstring curls: prone and sitting → progress 1–2 lb weights
- Calf raises 2 → 1 foot; up-on-toes walking (when full WB)
- Wobble boards with support: side-to-side, forward/backward
- Single leg stance 30–60 seconds (when full WB)
Modalities: Ice compression therapy as needed. Compex/muscle stimulation to assist muscle activation. Blood flow restriction (BFR) therapy during strengthening exercises.
Phase III — 3–6 Months
Strength & Conditioning
Brace & Weight Bearing
Ossur Cartilage Rebound unloading brace until 6 months for activity.
ROM
Full and pain-free.
Exercises
- Continue bike; add elliptical
- Stairmaster if adequate strength (no hip hiking when pressing down on step)
- Continue core strengthening (obliques, planks, Pilates)
- Progress leg extensions with weight as tolerated (pain-free arc)
- Sit to stand lower seat height → single leg (watch mechanics)
- Progress resistance on shuttle: strength & endurance, 2 → 1 leg
- Static lunge → dynamic lunge → lunge walking (within pain-free range)
- Bungee cord walking: forward, backward, side step, lunging → add speed/direction change
- Forward and lateral step-ups 2–4–6" and eccentric lateral step-down with control
- Squats and lunges on Dynadisc / Airex / BOSU (within range as tolerated)
- Continue hip strengthening: weights, pulleys, tubing; tubing kick-backs (mule kicks)
- Shuttle standing kick-backs (hip/knee extension)
- Supine Swiss ball bridge + knee flexion → 1 leg
- Hamstring curls: standing & sitting — weights/pulleys/bungee; eccentric heel drops 2 → 1 leg
- Continue wobble boards; add upper body skills (throwing, catching)
- Single leg stance on unstable surfaces (pillow, mini-tramp, BOSU, Airex, Dynadisc)
- Single leg stance with upper body patterning specific to patient goals
- Standing 747s: eyes open/closed → progress to mini trampoline
Modalities: Blood flow restriction (BFR) therapy during strengthening exercises.
Phase IV — 6+ Months
Return to Activity / Light Sport
Brace & Weight Bearing
As tolerated per surgeon guidance.
ROM
Full and pain-free.
Exercises
Impact activities such as jogging/running may commence from 6 months onwards.
- Begin jogging/running programme once full ROM regained with quiet knee and adequate neuromuscular control
- Agility: cariocas/grapevine, figure 8s around cones, ladder drills, lateral shuffle cone-to-cone
- Side-to-side steps/jumps on BOSU
- Line jumping: backward/forward/side-to-side → progress to diagonals/combined patterns; 2 → 1 leg
- Jumping: tuck jumps, box jumps, long jumps
- Skipping rope: double and single leg
- Hopping: single-leg distance, 6 m timed, triple hop, cross-over — 2 → 1 leg
- Sport-specific multi-directional drills and contact when adequate core/lower extremity patterning (stop-and-go, sideways/backwards drills, sprinting with cutting and pivoting)
* Timelines are approximate. Exercises are given as examples only and should be directed by your physiotherapist. Progression is criteria-based and directed by your physiotherapist in conjunction with Mr Getgood's clinical review. Individual recovery varies.
Frequently Asked Questions
Supporting Evidence
Noteworthy Publications from Mr Getgood Pertaining to Meniscal Allograft Transplantation
Beel W, Firth AD, Tulloch S, Abdelrehman T, Olotu O, Bryant D, et al. Extrusion After Meniscal Allograft Transplantation Is Lower or Equal With Bony Compared With Soft-Tissue Root Fixation: A Systematic Review. Arthroscopy. 2025;41(3):785–97 e2.
Novaretti JV, Patel NK, Lian J, Vaswani R, de Sa D, Getgood A, et al. Long-Term Survival Analysis and Outcomes of Meniscal Allograft Transplantation With Minimum 10-Year Follow-Up: A Systematic Review. Arthroscopy. 2019;35(2):659–67.
Hewison C, Kolaczek S, Caterine S, Berardelli R, Beveridge T, Lording T, et al. Peripheral fixation of meniscal allograft does not reduce coronal extrusion under physiological load. Knee Surg Sports Traumatol Arthrosc. 2019;27(6):1924–30.
Getgood A, LaPrade RF, Verdonk P, Gersoff W, Cole B, Spalding T, et al. International Meniscus Reconstruction Experts Forum (IMREF) 2015 Consensus Statement on the Practice of Meniscal Allograft Transplantation. Am J Sports Med. 2017;45(5):1195–205.
Spalding T, Getgood A. Defining outcome after meniscal allograft transplantation: Is buying time a valid measure of success? Knee Surg Sports Traumatol Arthrosc. 2016;24(5):1424–6.
Kempshall PJ, Parkinson B, Thomas M, Robb C, Standell H, Getgood A, et al. Outcome of meniscal allograft transplantation related to articular cartilage status: advanced chondral damage should not be a contraindication. Knee Surg Sports Traumatol Arthrosc. 2015;23(1):280–9.
Other Noteworthy Publications Pertaining to Meniscal Allograft Transplantation
Ahmed I, Khatri C, Spalding T, Smith N. Meniscal allograft transplantation in patients with substantial cartilage disease led to a sustained long-term improvement in patient-reported outcome measures. Knee Surg Sports Traumatol Arthrosc. 2025;33(8):2771–80.
Wang Z, Credille K, Swindell H, McCormick JR, Darbandi A, Alzein M, et al. Concomitant Treatment of High-Grade Cartilage Lesions Mitigates Risk of Meniscal Allograft Transplant Failure. Arthroscopy. 2024;40(5):1703–13 e2.
Cvetanovich GL, Christian DR, Garcia GH, Liu JN, Redondo ML, Yanke AB, et al. Return to Sport and Patient Satisfaction After Meniscal Allograft Transplantation. Arthroscopy. 2020;36(9):2456–63.






